IN MINNESOTA, DIRECT SERVICE PROVIDERS DESCRIBE A WORSENING OPIOID CRISIS, WHILE EXPERTS AND MEDIA CELEBRATE FABRICATED GAINS
Community workers serving high-risk drug users report the usual: undercounted nonfatal overdoses, naloxone saves dropping OD deaths, no gains on reducing high-risk opioid use
by Clark Miller
Published October 30, 2026
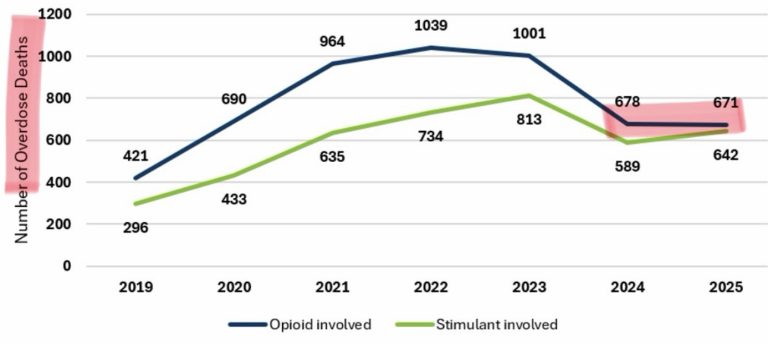
The celebratory news headline couldn’t be much more clear, heralding three straight years of declining opioid involved deaths.
That headline could definitely be less deceptive and more accurate, though, those qualities important for information bearing on a worsening public health crisis.
Something like, “Minnesota opioid deaths stall after a large drop the previous year“, because, obviously, the only reasonable, ethical, appropriate response to that trend is to seek understanding of why it occurred and how to adjust approaches.
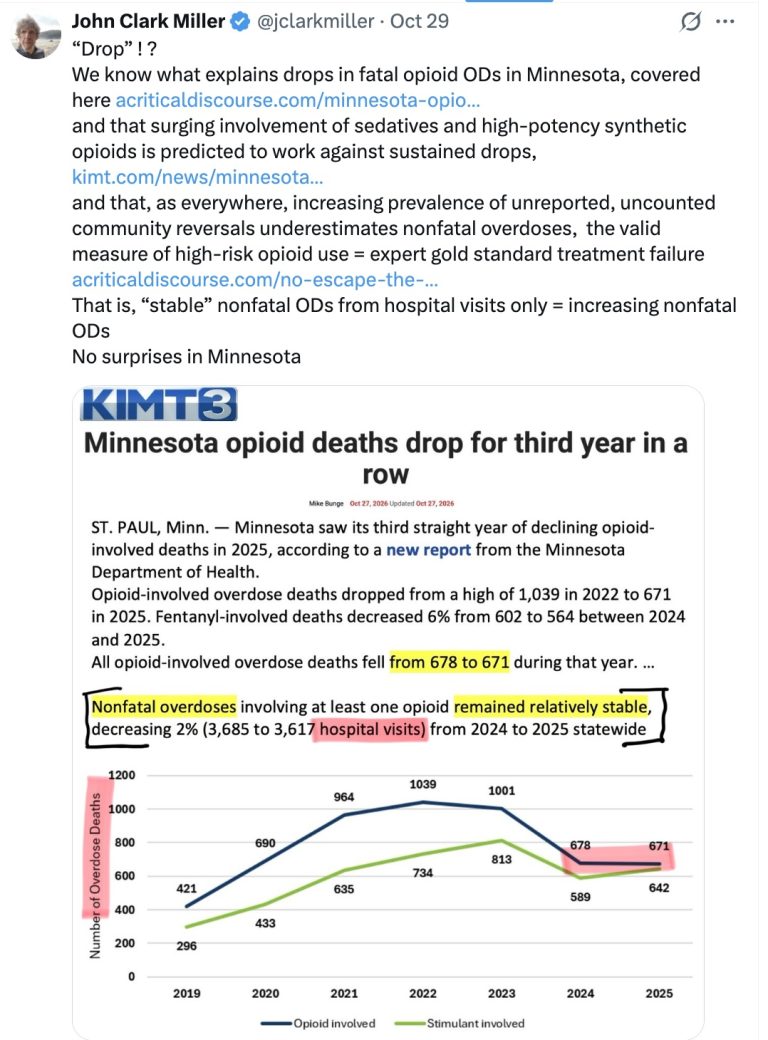
From the state report and adding to the picture, nonfatal opioid overdoses were not measured; that is, they were based on reports of overdoses survived and seen at hospitals. Those are a certain underestimate of nonfatal opioid overdoses, because in Minnesota, as essentially everywhere else, intensive naloxone campaigns have shifted reversals of potentially fatal opioid overdoses away from emergency medical services and to community settings where they are very often not reported.
That’s important too. Why?
Because our need to find a way out of the lethal epidemic cannot rely on trends in fatal overdoses, those recent year drops established as due to desperate Narcan campaigns and their necessity thereby reflecting persistently surging high-risk opioid use.
And because that leaves nonfatal opioid overdoses – reflecting high-risk opioid use and therefore benefit or failure of gold-standard treatments – as the primary valid measure of a worsening of or progress against the crisis, taking us back to the increasing undercounts of nonfatal ODs and the invalidation of any use of nonfatal OD estimates that do not incorporate confident estimates of unreported community reversals.
And that’s why additional, direct-service reports from Minnesota are valuable and telling.
Like these, from community organizations providing direct services and with direct contact with high-risk opioid users, in an ABC local news report –
Monica Ziebell, the interim program manager for the Olmsted County Crisis Response Team, said the numbers were consistent the last few years but wouldn’t necessarily say that we’ve seen a great decline of fatal overdoses locally.
According to Ziebell, the data is harder to track because less people are calling law enforcement to report overdoses.
Ziebell pointed toward people having easier access to Narcan, a medication that quickly reverses an opioid overdose, as a main reason for fewer overdose calls.
According to MN Adult and Teen Challenge center director Matthew Miller, there’s been a decrease in opioid related deaths, however demand for treatment services is higher than it’s ever been.
The Minnesota Adult and Teen Challenge centers in Rochester are both at full capacity with the women’s facility holding a waiting list.
“There’s an overall awareness that is increasing as well as the availability of things like Narcan that is definitely decreasing the deaths. it’s not necessarily stopping the level of addiction, but it’s decreasing the fatalities,” said Miller.

[emphasis added]
“demand for treatment services is higher than it’s ever been … [Narcan is] not necessarily stopping the level of addiction, but it’s decreasing the fatalities”
Those direct observations from direct service providers in a community in Minnesota are an accurate description of trends across the U.S., described here and here and here, for example.
Narcan, of course, can do nothing to stop or moderate high-risk opioid use, can only provide harm reduction by reversing otherwise fatal opioid overdoses persistently occurring due to failure of existing treatments and approaches.
My take on X –